
Travel and Storage / August 13, 2026
How to Travel With Peptides: A Practical Storage Guide
A community member asked, “any advice on travel? leaving in one week for 3 weeks. Should I wait until I am at my destination for constitution? And for the flight home, will they spoil if not refrigerated?”
The honest short answer is that “peptides” do not share one travel rule. The answer depends on the exact product, whether it is dry or reconstituted, the label or pharmacy instructions, the highest temperature it reaches, and the total time outside its required range.
Educational, not medical advice. Ask the prescribing clinician, dispensing pharmacist, or manufacturer about the exact product before changing its preparation, storage, or schedule.
The Short Answer
Do not make the decision from flight time alone
Waiting until you arrive to reconstitute can make the outbound trip simpler, but only if the unmixed product's instructions allow the trip you have planned. Dry powder is not automatically shelf-stable, and reconstitution can start a new storage or beyond-use clock. A three-week trip is long enough that you need a plan for the stay and the return flight, not only the first airport day.
Likewise, “Will it spoil on the way home?” cannot be answered by counting hours in the air. A pharmacist or manufacturer will want the product name, preparation state, time outside the instructed range, highest known temperature, and any freezing or direct-light exposure. The vial's appearance cannot prove potency or sterility.
Start with our label-backed peptide storage guide. Its U.S. sources were checked August 2, 2026, but the label and pharmacy instructions in front of you still control.
From the community
Ask travelers who have packed the routine
Packing details are exactly the kind of practical question our members compare. Join the conversation, then confirm product-specific advice with your pharmacist or clinician.
Join our WhatsApp communityBefore You Reconstitute
Choose the simpler plan only after you know the rules
Write down the answers to these questions before deciding where to reconstitute:
- What is the exact product, concentration, and dosage form?
- Is it an FDA-approved product, a pharmacy-compounded preparation, or a research-labeled product?
- What does the package insert or dispensing label say about unopened and in-use storage?
- What changes after reconstitution, including the beyond-use date?
- Can your destination provide reliable refrigeration without freezing the vial?
- What will you do during hotel changes, day trips, and the return flight?
If the written instructions do not answer those questions, call before departure. Do not borrow the 21-, 28-, 30-, or 56-day room-temperature rule from a different branded medication. Compounded and reconstituted products can have different formulations, containers, and beyond-use dates.
Cooling Gear
Our travel-bag pick, with one important limit
For heat protection when the product's instructions allow room-temperature storage, we recommend the FRIO cooling wallet. It activates with water, packs more easily than a hard cooler, and can be reactivated during a longer trip.
A FRIO wallet is not a refrigerator. The manufacturer says it keeps in-use insulin at 64.4°F to 78.8°F for at least 45 hours in an ambient temperature of 100°F. Standard refrigerated storage for many products is 36°F to 46°F. Use FRIO for another medication only if its instructions or the pharmacist or manufacturer confirms that the FRIO range is acceptable. Read the FRIO instructions before use.
Affiliate disclosure: We may earn a commission if you buy through the Amazon link. The price you pay does not change.
If the product must remain at 36°F to 46°F, ask the pharmacist or manufacturer what validated travel container to use. Keep medication from touching frozen packs unless the instructions specifically allow it. Freezing can be as consequential as excess heat.
Airport Checklist
Pack it in your carry-on and make screening easy
For flights departing from the United States, TSA permits medically necessary medication in carry-on bags. It also permits unused syringes when they accompany injectable medication. Declare medically necessary liquids and cooling supplies at the checkpoint, and expect them to receive additional screening.
- Medication in its original labeled container when possible.
- A copy of the prescription or clinician letter if the destination recommends it.
- Unused syringes beside the injectable medication, plus a plan for used sharps.
- Cooling supplies that match the product's required range.
- A thermometer or temperature logger when the product requires a narrow range.
- Pharmacy, manufacturer, and clinician contact information.
- Enough supplies for delays, without exceeding import limits at the destination.
Keep the kit with you rather than in checked baggage, where you cannot monitor delays, heat, or freezing. Check the current airline, customs, and destination-country rules before every international trip. U.S. screening rules do not override another country's import laws.
At Your Destination
Treat the hotel refrigerator as unverified until you check it
A small hotel refrigerator can run warm, freeze items near the cooling plate, switch off when you leave the room, or be cleared during housekeeping. Ask the hotel how the unit works, check the temperature, and keep the medication in a labeled secondary container away from the freezer plate. Do not leave it in a hot car, direct sunlight, or a sealed bag that defeats an evaporative cooler's airflow.
Record the reconstitution date, local dose times, room changes, and any known temperature excursions. Time-zone changes can also move a scheduled dose. Ask the prescribing clinician how to handle the schedule rather than improvising a new interval.
If Something Went Wrong
Do not guess from how the vial looks
If the medication became warm, froze, lost its label, or sat outside the required range, set it aside. Write down when the excursion began and ended, the highest and lowest known temperatures, the product and lot, whether it was dry or reconstituted, and whether it was exposed to light.
Call the dispensing pharmacist or manufacturer with that record. Returning the product to a refrigerator does not reset the clock, and a clear-looking solution does not prove that it remains potent, sterile, or safe.
Quick Plan
The one-week travel prep schedule
- Today: Photograph the label and call about dry, mixed, and travel storage limits.
- Within 48 hours: Check airline, TSA, customs, and destination rules.
- Three days before: Test the cooler and thermometer without the medication inside.
- Two days before: Build the schedule across time zones and save contact details.
- Travel day: Pack the labeled kit in your carry-on and declare supplies for screening.
- During the trip: Log preparation dates, storage changes, and temperature excursions.
- Before the return flight: Recheck the product's remaining allowed time and cooling plan.
Frequently Asked Questions
Peptide travel questions, answered
Should I wait until I reach my destination to reconstitute a peptide?
There is no universal rule. Waiting can simplify the outbound trip only when the product instructions and your clinician or dispensing pharmacist confirm that the unmixed product can be transported that way. A dry vial still has storage requirements, and a reconstituted vial can have a different beyond-use date and temperature limit.
Will a peptide spoil on the flight home if it is not refrigerated?
Flight time alone cannot answer that question. Check the exact product, preparation state, label or pharmacy instructions, total time outside the required range, highest known temperature, and whether it froze or sat in direct light. If the temperature history falls outside the instructions, set it aside and contact the dispensing pharmacist or manufacturer.
Can I bring peptide medication and syringes through TSA?
TSA permits medically necessary medications in carry-on bags and allows unused syringes when they accompany injectable medication. Declare medically necessary liquids and cooling supplies for inspection. TSA recommends labeling medication, and international, airline, and destination-country rules can differ.
Does a FRIO wallet keep peptides refrigerated?
No. FRIO says its evaporative wallet keeps in-use insulin at 64.4°F to 78.8°F for at least 45 hours in an ambient temperature of 100°F. It is not a 36°F to 46°F refrigerator substitute. Use it for another medication only when that medication's instructions or a pharmacist or manufacturer confirms that range is acceptable.
Sources
Travel and storage references
Additional research context by Jay Spall
Further evidence and practical limits
Key facts
| What you actually want to know | Direct answer |
|---|---|
| Does TSA treat powder and reconstituted peptide the same? | No. Lyophilized powder is a solid and isn't governed by the carry-on liquids limit. Once you add bacteriostatic or sterile water it becomes a liquid, subject to the 3.4 oz (100 mL) per-container rule (a screening policy figure, not a research finding from the sources cited here), unless declared as medically necessary. |
| Does declaring a research-use-only vial as "medically necessary" actually work? | Genuinely unclear. The exemption is built around presenting something as medication for personal use. A vial labeled "not for human consumption" undercuts that framing no matter what's dissolved in it. |
| Is the checkpoint the real legal risk? | Usually not. The bigger exposure sits at your destination's border, where unapproved or unlabeled products are governed by import law that has nothing to do with TSA's screening rules. |
| Is a cloudy vial ruined? | Not necessarily. Cloudiness can mean contamination, but it can also come from temperature-driven precipitation or protein aggregation, and those are different problems with different consequences. |
| Does the generic "2 mL water, count insulin units" chart give me the right dose? | Only if your vial's total mg happens to match the chart's built-in assumption. Units are just the syringe barrel divided into 100 marks per mL; they say nothing about your peptide's concentration until you calculate it. |
| Should I refrigerate a mixed vial while traveling? | Where possible, yes, and keep it with you in the cabin. Checked baggage holds see wider, less controlled temperature swings than cabin air, and that's where reconstituted peptide actually loses potency. |
5 sources cited. View sources
Powder versus liquid: the rule TSA actually applies
Airport screening classifies substances by physical state, not by identity. A sealed vial of lyophilized powder is a solid; it isn't measured against the carry-on liquids volume cap, though it may draw extra scrutiny at the X-ray or a swab test. The moment you reconstitute it with diluent, it becomes a liquid and falls under the standard container-size rule. Travelers can exceed that limit for medically necessary liquids if they declare them at screening, an exemption long used by people carrying insulin, itself a reconstituted peptide hormone drug that has been transported this way for decades [3]. That precedent is why the powder-versus-liquid framing gets repeated so confidently online. It's also where the advice usually stops, right before the part that actually matters.
The exemption assumes you have medication, not a research compound
The medically-necessary-liquid exemption exists for prescribed drugs a traveler can present as their own medication. A screening officer isn't adjudicating whether your vial is a legal drug; they're applying a volume exception. That doesn't resolve the underlying labeling question. A product marked for research use only, not for human administration, doesn't fit the framing the exemption was built for, regardless of what a traveler declares at the checkpoint. This same friction shows up elsewhere: patients facing regulatory lag on approved indications sometimes resort to costly personal importation of unapproved products, a pattern documented outside the peptide space entirely but structurally identical to it [2]. The checkpoint isn't where that ambiguity gets settled. Customs and import law at your destination is, and that varies by country and by substance in ways no TSA policy addresses.
Temperature, not the flight, is the real stability risk
Reconstituted peptide is a biologic in solution, and biologics degrade with heat exposure and with time outside their intended storage range. Evidence-based guidance on how much room-temperature exposure a refrigerated biologic can tolerate before losing potency remains limited even for well-characterized, approved drugs, despite these excursions happening constantly in real-world handling [1]. For insulin specifically, a peptide hormone drug studied more than most, storage recommendations are often not met once the product leaves controlled distribution, and there's a documented gap between package-insert guidance and what actually happens after a vial is carried around by its owner [3]. Mean kinetic temperature modeling shows that shelf-life loss from an excursion depends heavily on how long the excursion lasts and what temperature range it hits, not just whether one occurred [4]. Practically, a checked bag can sit on a tarmac in extreme heat or a cold cargo hold; a cabin bag experiences a controlled, human-tolerable temperature range for the entire flight. That difference matters more to your vial than anything TSA does at the checkpoint.
Doing the math: from vial to syringe units
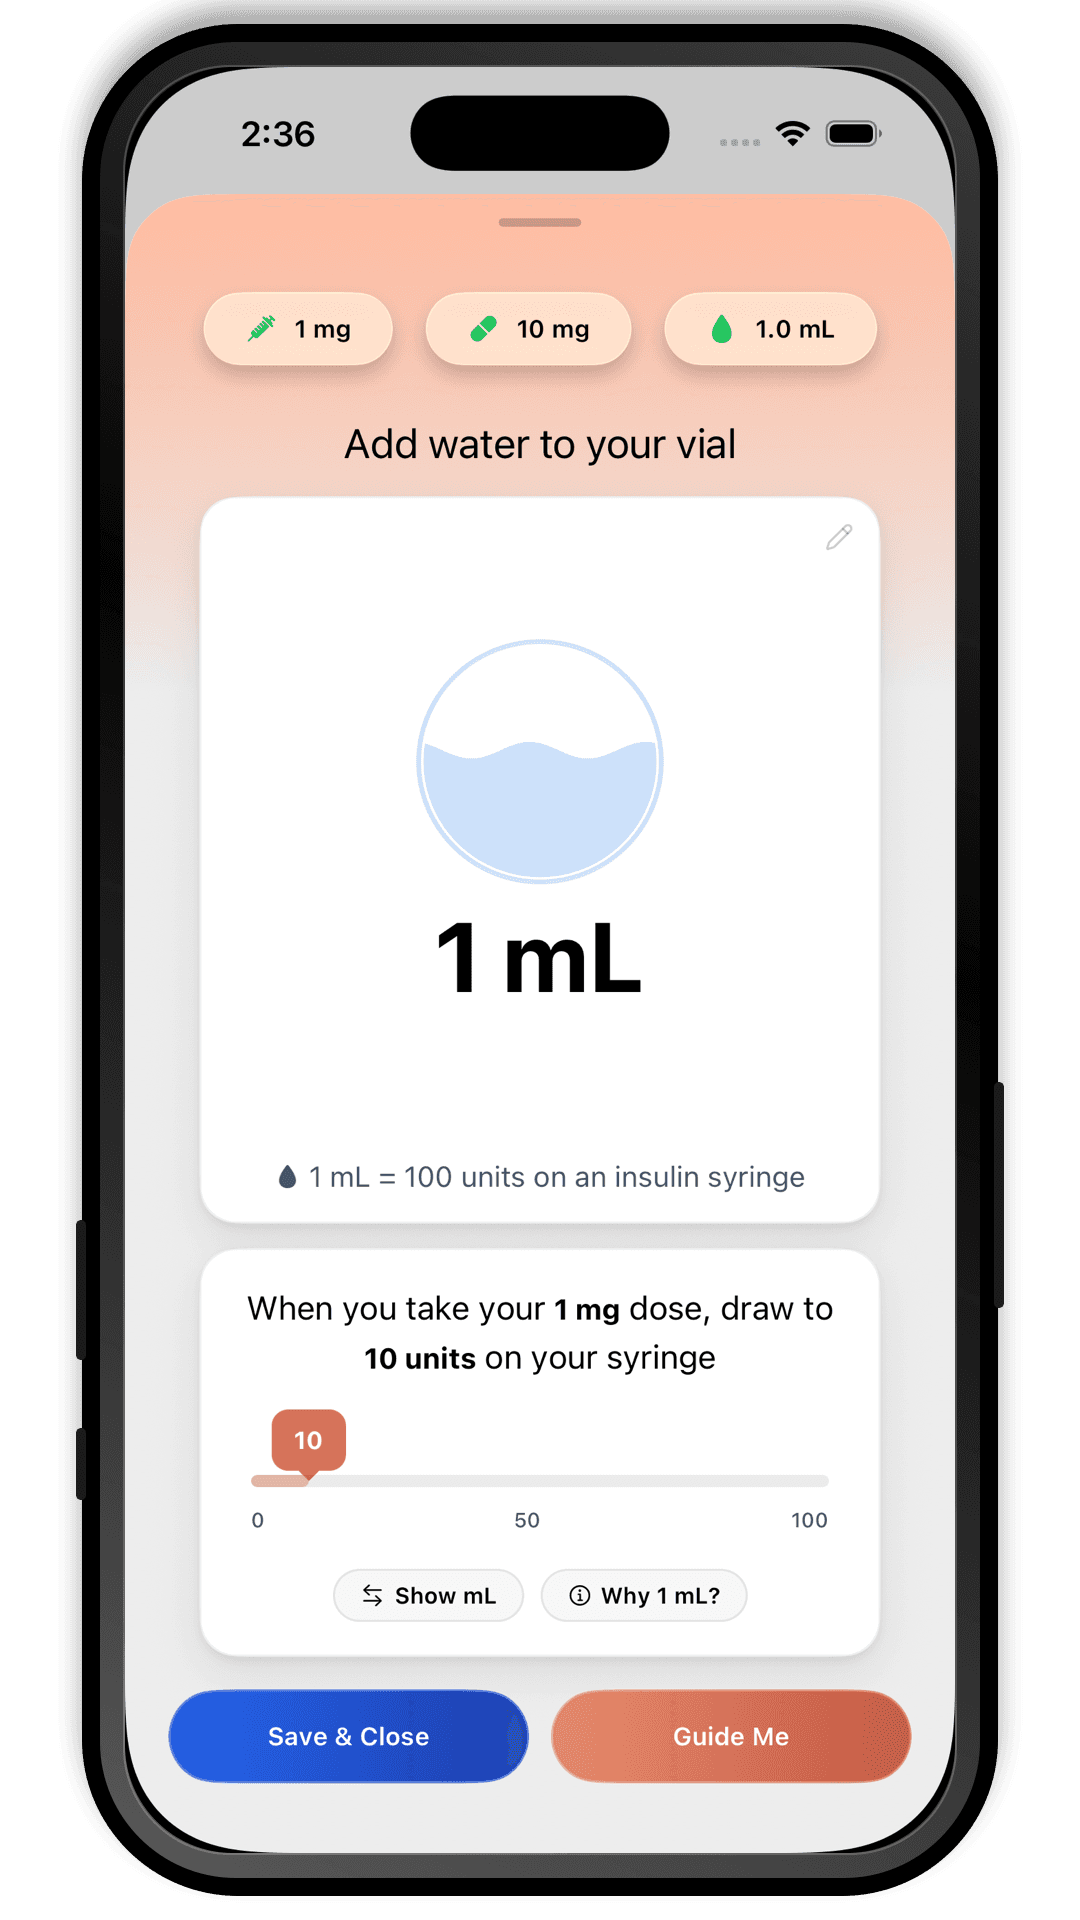
A "2 mL of diluent" instruction and a units chart are useless without knowing your vial's actual peptide content. The calculation has three steps. First, divide total peptide mass by diluent volume to get concentration: a 5 mg vial reconstituted with 2 mL yields 2.5 mg/mL, or 2,500 mcg/mL. Second, divide your target dose by that concentration to get the volume to draw: a 250 mcg target divided by 2,500 mcg/mL is 0.1 mL. Third, convert to syringe units: a standard U-100 insulin syringe divides 1 mL into 100 units regardless of what's in the barrel, a convention that exists because insulin dosing has historically been standardized this way [3], so 0.1 mL reads as 10 units. Change the diluent volume or the vial's stated mg content and every downstream number changes with it. No chart can do that math for you; only your own vial's label can.
Cloudy vial: what it can and can't tell you
Visual cloudiness has more than one cause. It can indicate bacterial growth or endotoxin activity, a real sterility problem. It can also result from temperature-driven precipitation after an excursion, from protein aggregation at higher concentrations, or from the diluent itself. Data on refrigerated biologics show that potency loss and physical changes both track with the degree and duration of temperature exposure, not with a single visible threshold [1][4]. None of the sources here test peptide research compounds specifically for this, so there's no visual rule that reliably separates "cosmetically off but fine" from "actually compromised." Discarding a vial on appearance alone is the cautious choice, not a scientifically settled one.
What's genuinely unknown
Guidance on acceptable temperature excursion time for refrigerated biologics is inconsistent even among manufacturers and regulators for approved drugs [1], and real-world storage behavior for peptide hormone products diverges from label instructions in ways that remain poorly documented [3]. Mean kinetic temperature calculations rely on default kinetic parameters rather than compound-specific decay data [4], and cold-chain competency frameworks emphasize that trained handling matters as much as equipment, which has no clean airport-travel analogue [5]. No source here measures airport-specific transit outcomes, TSA's practical handling of unlabeled research vials, or destination-country legal status for personally carried peptide products. That gap is the honest answer, not an oversight in this article.
Sources
-
Aleidi FA, Alomair S, Alharbi H (2025). Stability of Refrigerated Medications at Room Temperature: Implications for Transport, Delivery, and Patient Safety. Cureus. PMID: 41020019. pubmed.ncbi.nlm.nih.gov/41020019
-
Inoue S, Ozaki A, Hakariya H (2025). Addressing the drug development challenge for rare pediatric diseases in Japan: a case study of isotretinoin. Invest New Drugs. PMID: 40694216. pubmed.ncbi.nlm.nih.gov/40694216
-
Heinemann L, Braune K, Carter A (2021). Insulin Storage: A Critical Reappraisal. J Diabetes Sci Technol. PMID: 31994414. pubmed.ncbi.nlm.nih.gov/31994414
-
Jenkins D, Cancel A, Layloff T (2022). Mean kinetic temperature evaluations through simulated temperature excursions and risk assessment with oral dosage usage for health programs. BMC Public Health. PMID: 35164726. pubmed.ncbi.nlm.nih.gov/35164726
-
Kartoglu U, Vesper J, Teräs H (2017). Experiential and authentic learning approaches in vaccine management. Vaccine. PMID: 28364938. pubmed.ncbi.nlm.nih.gov/28364938

The Peptide App
Track protocols, doses, and reconstitution in one place.
Save your calculations, set reminders, log doses, and keep outcome notes — free to start.
 or scan the QR code →